CGM in Type 2 Diabetes Without Insulin: NEJM Trial for USMLE
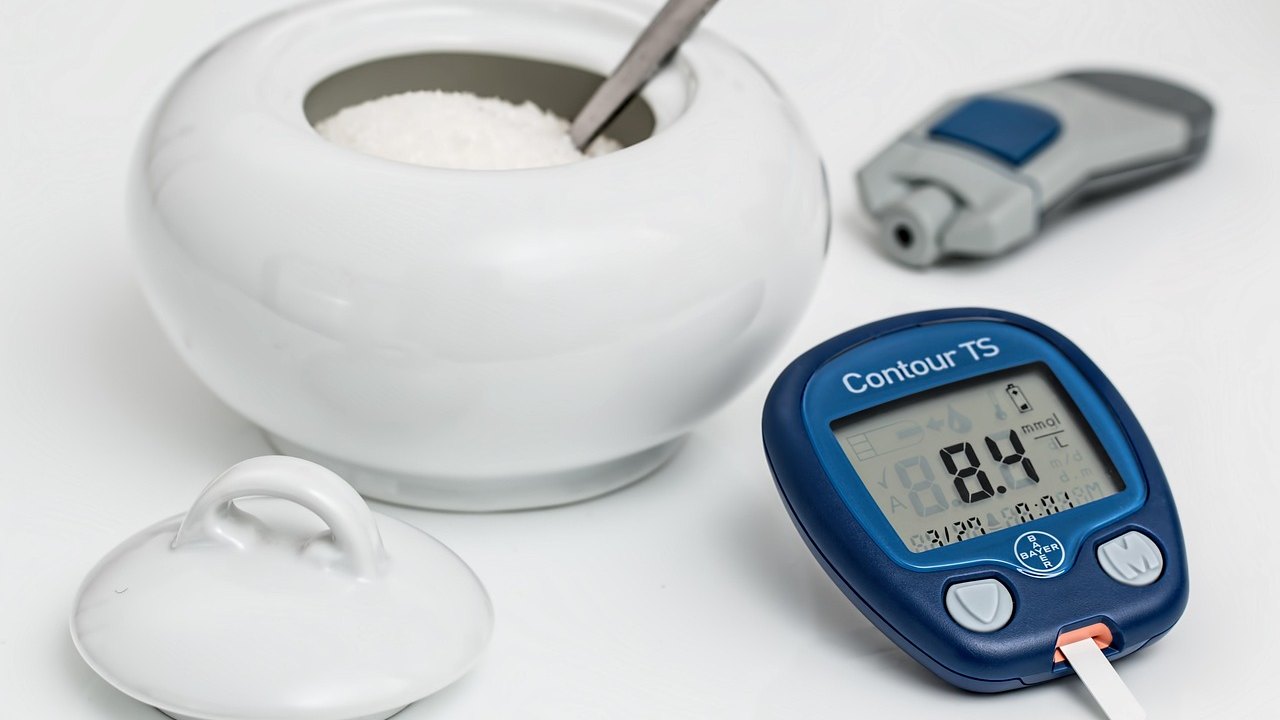
A randomized trial in the New England Journal of Medicine tested continuous glucose monitoring (CGM) in adults with type 2 diabetes who do not take insulin. Over 26 weeks, CGM users spent about five more hours per day in their target glucose range than people receiving routine care. A1c also improved more with CGM. This is a group for whom CGM has not been well studied.
What happened
Tamara Oser, MD, of the University of Colorado Anschutz, and colleagues enrolled 283 adults with type 2 diabetes who were not using insulin. Participants came from 22 primary care practices in the United States and were followed for 26 weeks. According to the authors, this is the first large, multicenter randomized controlled trial of CGM effectiveness and safety in this population.
The reported results:
- CGM users spent roughly five additional hours per day in the target glucose range compared with routine care. By simple arithmetic, that is about 21% of a 24-hour day.
- The between-group difference in A1c was 0.9 percentage points in favor of CGM. The authors say this exceeds the threshold generally considered clinically meaningful.
- Nearly twice as many CGM users reached an A1c below 7%.
The trial enrolled patients exclusively through primary care, where most Americans with type 2 diabetes are treated. The authors say this makes the findings relevant to everyday practice. They estimate that about 20 million US adults have type 2 diabetes and do not take insulin.

Why it matters
CGM has mostly been associated with insulin therapy. The American Diabetes Association (ADA) Standards of Care rate the evidence for CGM in insulin-treated patients as Level A, the highest rating. For people who do not take insulin, the recommendation rests on Level C evidence, which reflects limited research. The investigators hope these data will help close that gap, strengthen guidelines, and support insurance coverage.
CGM uses a small body-worn sensor to track glucose day and night. Patients can see how food, activity, and other habits affect their glucose. The authors suggest that people with type 2 diabetes who don't use insulin discuss CGM with their primary care providers. That is the authors' general suggestion, not individual advice.
What to know for the USMLE — type 2 diabetes and glucose monitoring
- Pathophysiology of type 2 diabetes: peripheral insulin resistance (muscle, liver, adipose tissue) plus progressive beta-cell dysfunction. Islet amyloid (amylin) deposition is a classic histologic finding.
- Hemoglobin A1c reflects nonenzymatic glycation of hemoglobin and tracks average glucose over about 2–3 months, matching red cell lifespan (~120 days). The source describes it as approximately three months.
- A1c can be unreliable when red cell turnover is altered. It reads falsely low in hemolytic anemia, after blood loss or recent transfusion, and in some hemoglobinopathies. Iron deficiency can falsely raise it. This is a common Step 1 and Step 2 CK trap, and CGM metrics sidestep it.
- Diagnostic thresholds: A1c ≥6.5%, fasting glucose ≥126 mg/dL, 2-hour OGTT glucose ≥200 mg/dL, or random glucose ≥200 mg/dL with symptoms. Prediabetes is A1c 5.7–6.4%.
- CGM measures interstitial glucose, not plasma glucose. Readings lag blood glucose by several minutes, which matters during rapid changes.
- Time in range (TIR): the standard international consensus range is 70–180 mg/dL, with a common goal of more than 70% of the day in range. The news source does not state which range or targets this trial used, so check the paper for specifics.
- Time below range is the safety counterpart. Hypoglycemia matters most with insulin and sulfonylureas. The source does not report hypoglycemia results from this trial.
- Complications of chronic hyperglycemia: microvascular (retinopathy, nephropathy, neuropathy) and macrovascular (coronary, cerebrovascular, and peripheral artery disease). The quoted authors name heart disease, kidney disease, and vision loss.
- Pharmacology refresher: metformin is first-line, since it decreases hepatic gluconeogenesis and carries a risk of lactic acidosis. SGLT2 inhibitors and GLP-1 receptor agonists are favored when ASCVD, heart failure, or CKD is present. Sulfonylureas raise hypoglycemia risk.
- Evidence grading: know that ADA evidence levels (A through E) reflect study quality. Level A means well-powered randomized trials. Level C means weaker data such as observational studies or expert opinion.
- Exam logic: in a stem about a patient with type 2 diabetes who is not at goal, think about adherence, lifestyle, medication escalation, and self-monitoring together. Technology complements these and does not replace them.
Limitations
- Surrogate outcomes. Time in range and A1c are surrogate markers. The source does not report effects on complications, cardiovascular events, or mortality. A 26-week trial is too short to show those outcomes.
- Short follow-up. The source does not say whether the benefit persists after 26 weeks, or whether participants kept using CGM.
- Cost and access. The source material does not describe cost-effectiveness. The authors themselves point to insurance coverage as a barrier.
- Unreported details. The source does not give participants' background medications, the behavior changes behind the improvement, or the safety findings. Do not assume them.
- Open-label design is likely but not confirmed. Patients can see CGM data, so blinding is difficult. The source does not describe blinding, so read the full paper before drawing conclusions.
- Secondary reporting. This article relies on a press summary of the study, not the full paper (DOI: 10.1056/nejmoa2608571).
FAQ
Does CGM work in type 2 diabetes if you don't take insulin?
In this 26-week randomized trial of 283 adults, CGM users spent about five more hours per day in their target range than those receiving routine care. A1c was 0.9 percentage points better. These are surrogate outcomes, so longer-term benefits remain unproven.
What is "time in range" and why does it matter for the USMLE?
Time in range is the percentage of the day that glucose stays within a target band, typically 70–180 mg/dL in consensus guidelines. It complements A1c, which gives only an average and can be distorted by conditions that affect red blood cells. Expect to interpret both A1c and CGM-derived metrics in clinical vignettes.
Do these results change guidelines right away?
Not by themselves. The ADA currently cites Level A evidence for CGM in insulin-treated patients and Level C for non-insulin-treated patients. The authors hope the trial will strengthen guidelines and coverage. Whether and how guidelines change is up to the guideline bodies.
Key takeaways
- In a 26-week RCT of 283 primary care adults with type 2 diabetes not on insulin, CGM added about five hours per day in target range and improved A1c by 0.9 percentage points versus routine care.
- For the USMLE, connect this to A1c interpretation and its pitfalls, time in range, interstitial glucose, and ADA targets. Also review first-line type 2 diabetes pharmacology.
- Time in range and A1c are surrogates. The source reports no data on complications, mortality, or cost, so long-term benefit and value remain open questions.
Prepared by the project team from the source material. Not medical advice.